
Literature Database
NORSE Evidence Database
Building the largest systematic dataset on NORSE & FIRES worldwide.
470
Eligible articles
4,000+
Patients described
1,920+
Individual-level data
40+
Countries represented
About the database
Systematic database review
To advance understanding of NORSE and FIRES, the ICM NORSE team created a comprehensive, systematic evidence database. Using rigorous PRISMA methodology, we aggregated data from published literature to establish a large-scale, multi-center dataset enabling novel research and clinical insights.
PROSPERO registration
CRD420261395810
Results from this systematic database review will be published in peer-reviewed journals.
PRISMA methodology
How the database was built
Search strategy
A systematic PRISMA search was conducted using the key terms 'new-onset refractory status epilepticus', 'febrile infection-related epilepsy syndrome', 'NORSE', 'FIRES', and related variants.
- Search date
- Updated November 06, 2026
- Selection process
- Multi-step screening by two independent experts
- Study types
- Case reports, case series, reviews, pathophysiology studies, guidelines
Database scope
One of the largest aggregated NORSE/FIRES datasets worldwide.
- More than 4,000 patients described across all studies
- More than 1,920 patients with individual-level data available
- Both pediatric and adult populations
- Multi-country representation across 40+ countries
Eligible articles
470
188
Case reports
151
Case series
63
Reviews
30
Pathophysiology studies
40+ countries
Global research coverage
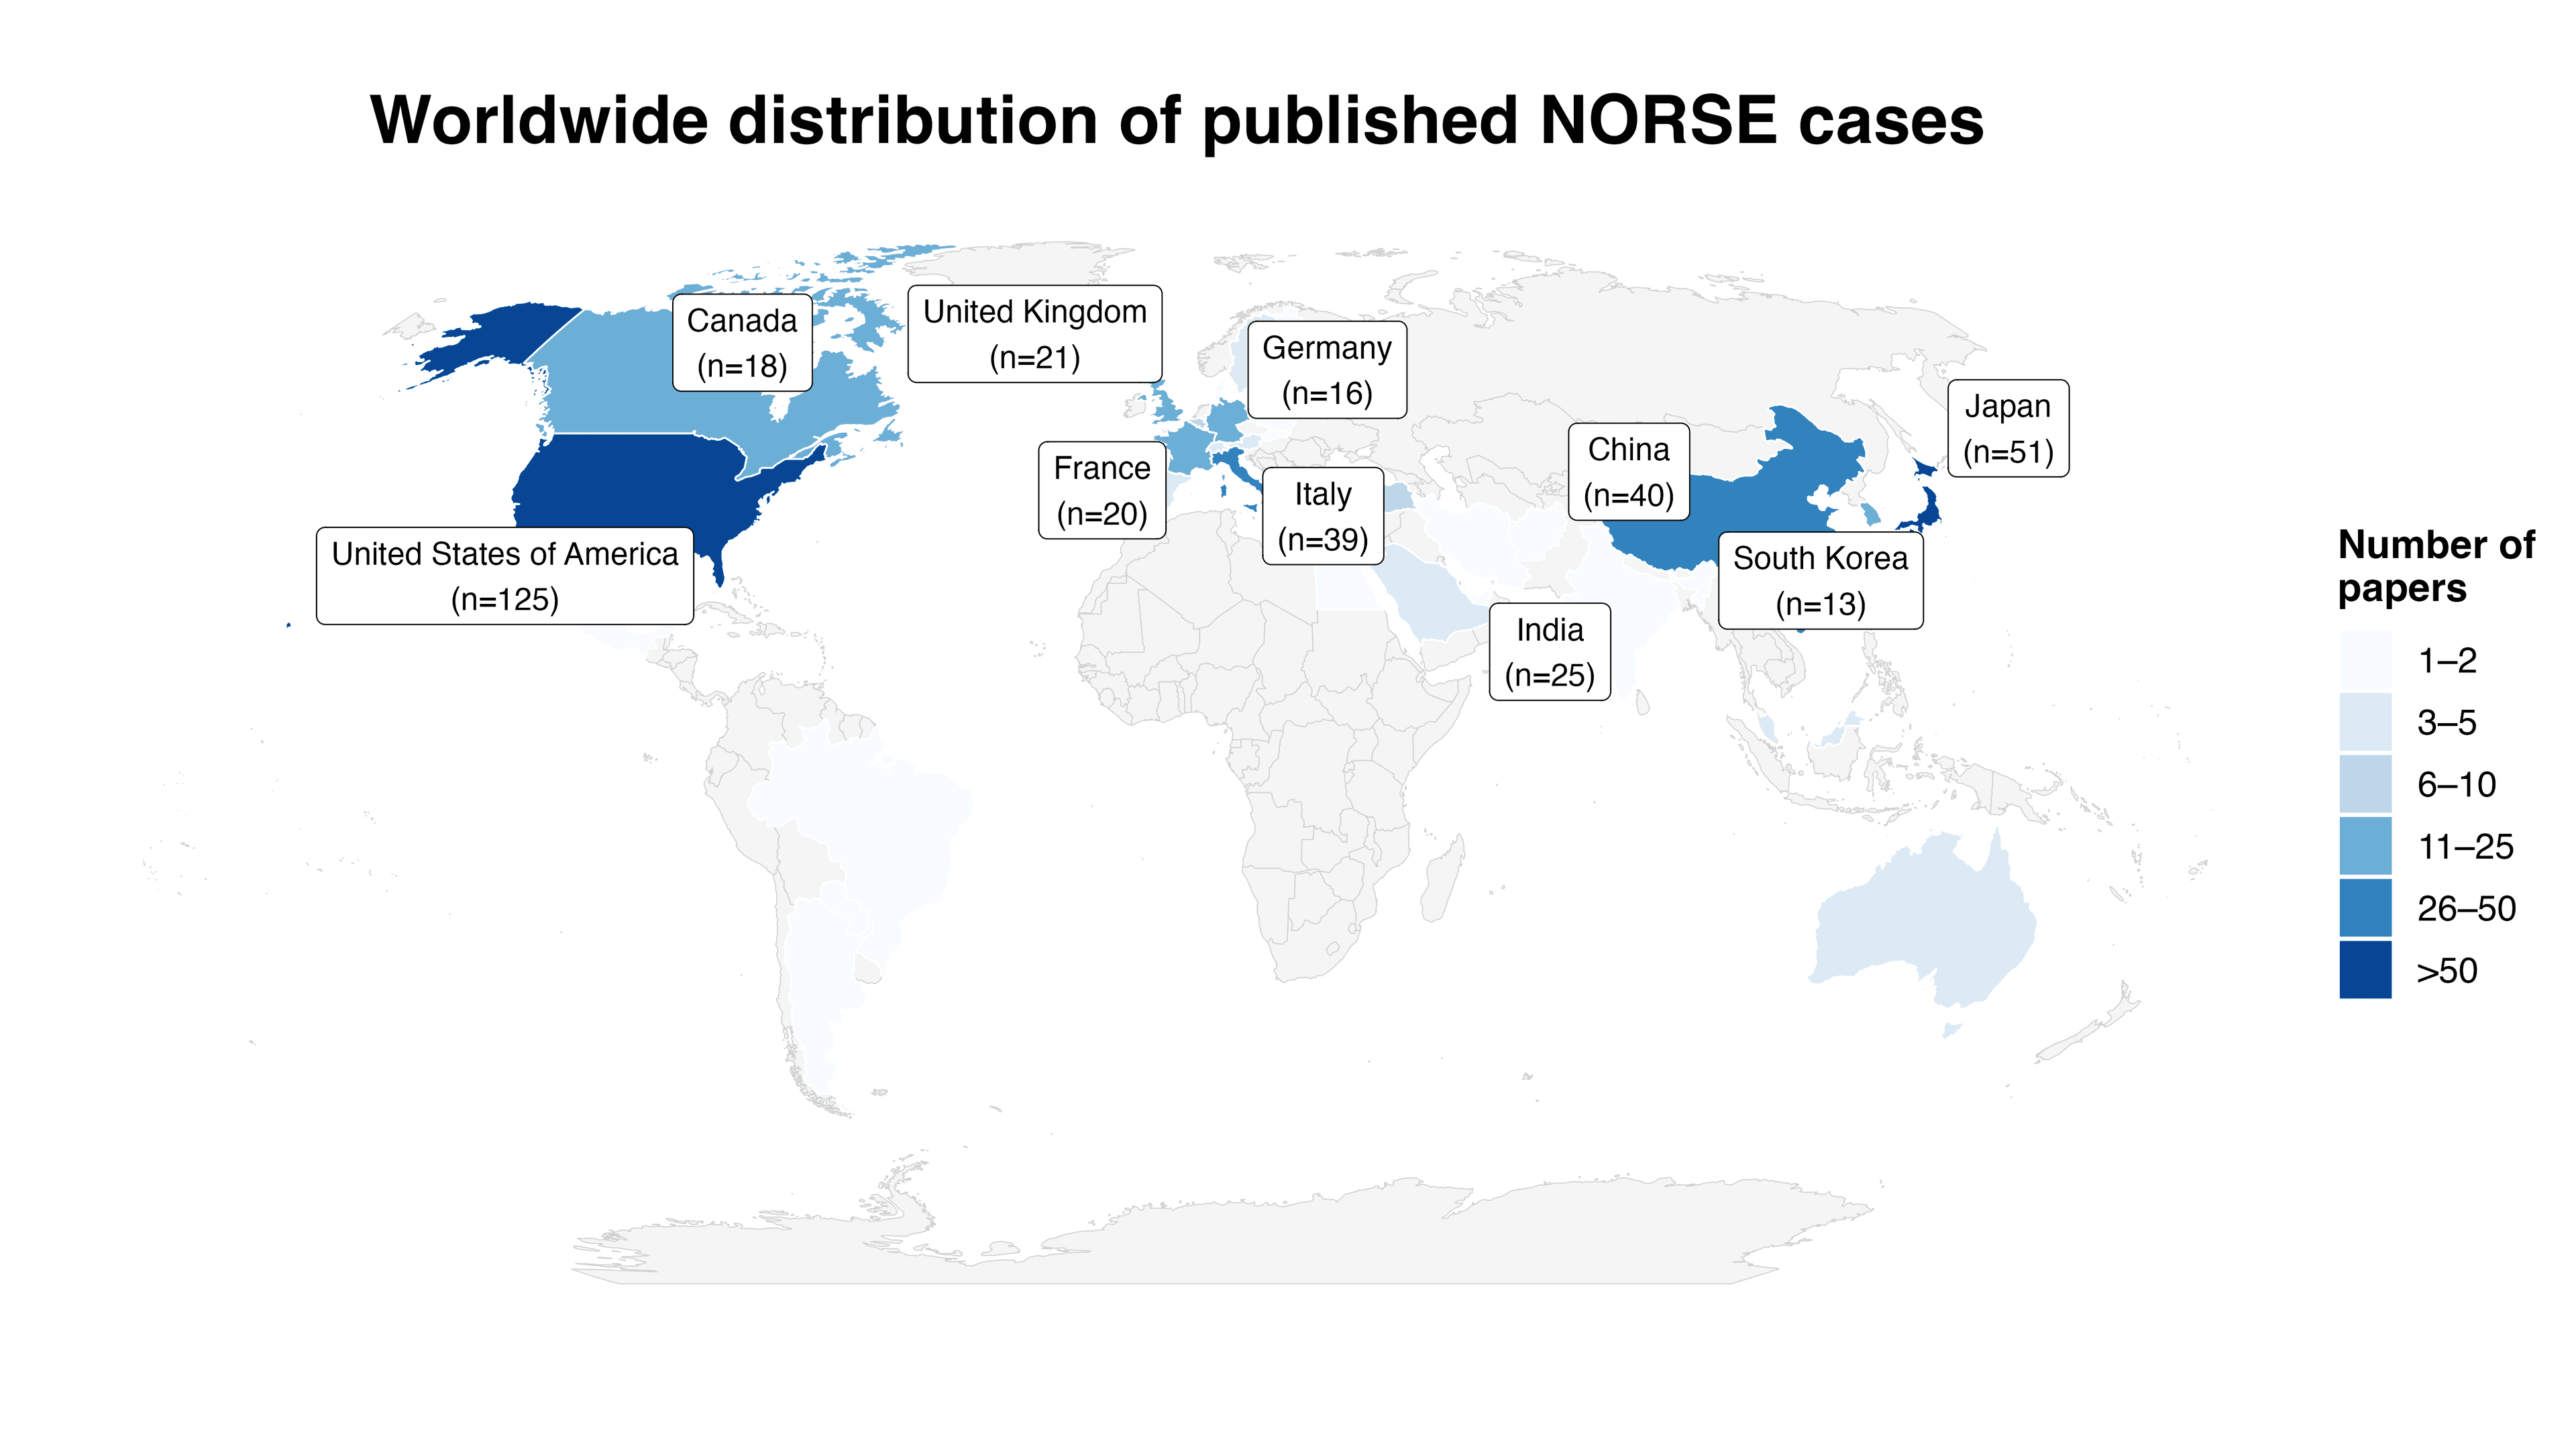
United States
125 articles
Japan
51 articles
China
40 articles
This international dataset reflects the global recognition of NORSE/FIRES as a significant clinical challenge.
Variables collected
Data extraction categories
ADemographics
Country, center, age group, age at presentation, sex
+
Demographics
Country, center, age group, age at presentation, sex
Country of enrollment, center of enrollment, age group (pediatric vs. adult), age at presentation, sex.
BPresentation
FIRES classification and prodromal symptoms
+
Presentation
FIRES classification and prodromal symptoms
FIRES classification
Prodromal symptoms: fatigue, respiratory symptoms, gastrointestinal symptoms, behavioral changes, headache, rash, consciousness alterations, memory disturbances, sleep disorders.
CEtiology
Cryptogenic, autoimmune, viral, genetic and other causes
+
Etiology
Cryptogenic, autoimmune, viral, genetic and other causes
Cryptogenic, autoimmune encephalitis (AIE), viral, genetic, and other identified causes with detailed characterization.
DTreatment
Immunotherapies, ASMs, anesthetics and other approaches
+
Treatment
Immunotherapies, ASMs, anesthetics and other approaches
Immunotherapies
- First-line: steroids, intravenous immunoglobulin, plasma exchange
- Second-line: anakinra, tocilizumab, intrathecal steroids, rituximab, cyclophosphamide, anti-JAK-STAT agents
- Dosages and time-to-initiation when available
Other therapeutic approaches
Ketogenic diet (KD), vagus nerve stimulation (VNS), electroconvulsive therapy (ECT), therapeutic hypothermia.
Antiseizure medications (ASMs)
Levetiracetam, phenobarbital, phenytoin, valproic acid, lacosamide, perampanel, and others.
Continuous intravenous anesthetic drugs (CIVADs)
Propofol, midazolam, ketamine/esketamine, thiopental, and inhaled anesthetics.
EWorkup
Blood, CSF, metabolic & genetic tests, imaging, EEG
+
Workup
Blood, CSF, metabolic & genetic tests, imaging, EEG
| Modality | Details |
|---|---|
| Blood tests | CBC, organ function, cytokines, auto-immune panels |
| CSF analysis | WBC/RBC counts, protein, glucose, oligoclonal bands, cytokines, viral/bacterial tests, auto-immune panels |
| Metabolic & genetic tests | Individual-level results |
| Neuroimaging | CT head and MRI findings during ICU stay |
| Advanced imaging | PET findings during ICU stay |
| Electrophysiology | EEG findings during ICU stay |
FClinical outcomes
Acute phase and long-term follow-up
+
Clinical outcomes
Acute phase and long-term follow-up
Acute phase
- ICU complications
- Need for tracheostomy
- Duration of status epilepticus, ICU length of stay, mechanical ventilation duration
- Mortality at discharge
Follow-up period
- Duration of follow-up
- Functional outcomes
- Mortality at last follow-up
- Development of post-NORSE epilepsy
- Status epilepticus recurrence and number of subsequent events
- Treatment during follow-up
- Chronic MRI, PET, and EEG findings
Collaborate with us
Are you interested in contributing clinical data or collaborating on analyses?